
For Informational Purposes Only
Bupivacaine TAP Blocks
Disclaimer: This article is intended solely for informational and educational purposes only. It does not constitute medical advice.
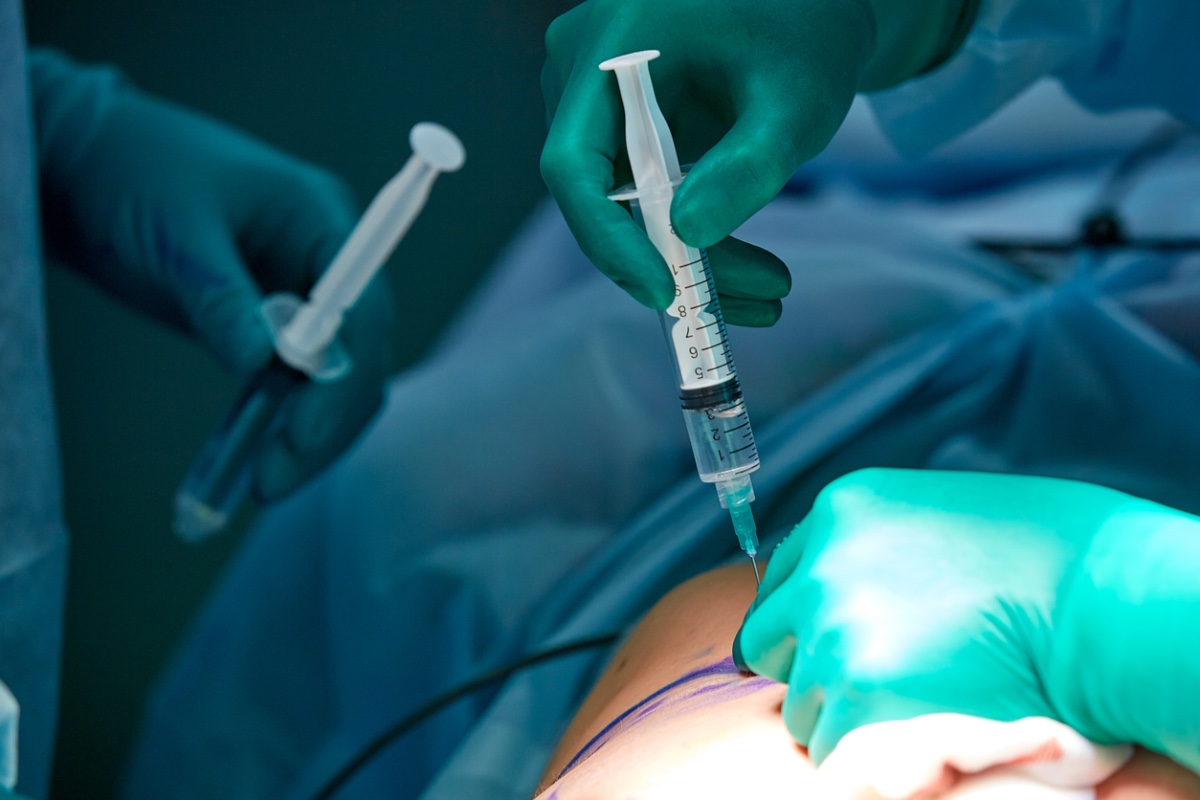
The transversus abdominis plane (TAP) block is a regional anesthetic technique increasingly utilized for postoperative pain management following abdominal surgery. By administering a local anesthetic, such as bupivacaine, into the fascial plane between the internal oblique and transversus abdominis muscles, the TAP block provides somatic analgesia to the anterolateral abdominal wall. This technique targets the thoracolumbar nerves supplying the abdominal musculature and overlying skin, typically involving spinal segments T6 through L1, depending on the injection approach. TAP blocks have become an important component of multimodal analgesia because of their potential to reduce opioid consumption and associated adverse effects while improving postoperative comfort (1).
Bupivacaine is a long-acting amide local anesthetic that reversibly inhibits voltage-gated sodium channels, preventing nerve impulse propagation. Its relatively prolonged duration of action makes it particularly suitable for postoperative analgesia. Ultrasound guidance facilitates accurate identification of abdominal wall musculature and visualization of local anesthetic distribution within the targeted fascial plane. Commonly utilized bupivacaine concentrations include 0.25% and 0.375%, although the appropriate concentration, volume, and total dose depend on patient characteristics and procedural requirements. Bilateral TAP blocks require particular attention to cumulative dosing because systemic absorption from the abdominal wall can produce clinically significant plasma concentrations (2).
Clinical investigations have demonstrated the analgesic benefits of bupivacaine TAP blocks across several abdominal surgical procedures. In a randomized, double-blind study involving patients undergoing cesarean delivery, Jadon et al. demonstrated that ultrasound-guided TAP blocks contributed to improved postoperative analgesia when incorporated into a multimodal pain management regimen. Similarly, Jain et al. evaluated ultrasound-guided TAP blocks in patients undergoing intraperitoneal onlay mesh repair and reported improved postoperative pain control. These findings support the effectiveness of TAP blocks for reducing incisional pain and potentially decreasing supplemental analgesic requirements (2).
Despite these benefits, TAP blocks have important limitations. Their analgesic effects primarily involve somatic abdominal wall pain, with less reliable coverage of visceral discomfort originating from intra-abdominal structures. Consequently, systemic analgesics, including acetaminophen and nonsteroidal anti-inflammatory medications, remain important in most cases. Effectiveness may also vary according to surgical procedure, injection location, anatomical variation, and technical expertise. Evidence from systematic reviews indicates that analgesic benefits are procedure-dependent, emphasizing the importance of individualized implementation rather than routine application in every abdominal operation (3).
Safety considerations remain essential when administering bupivacaine TAP blocks. Potential complications include vascular puncture, inadvertent intraperitoneal injection, infection, hematoma formation, and local anesthetic systemic toxicity. Toxicity may manifest as neurological disturbances, seizures, cardiac conduction abnormalities, or cardiovascular collapse. Ultrasound guidance, careful dose calculation, incremental injection, and appropriate monitoring help mitigate these risks. Liposomal bupivacaine formulations have also been investigated to prolong analgesia; however, systematic evidence has not consistently demonstrated clinically meaningful superiority over conventional local anesthetics across regional anesthesia applications (4).
Bupivacaine TAP blocks are a valuable opioid-sparing intervention within contemporary perioperative pain management. Their favorable analgesic potential, compatibility with ultrasound-guided techniques, and integration into multimodal protocols support their use in appropriately selected patients. Continued research should clarify optimal dosing strategies, procedure-specific efficacy, and comparative effectiveness against alternative regional anesthesia techniques to maximize postoperative recovery while maintaining patient safety.
References
- Jadon A, Jain P, Chakraborty S, et al. Role of ultrasound guided transversus abdominis plane block as a component of multimodal analgesic regimen for lower segment caesarean section: a randomized double blind clinical study. BMC Anesthesiol. 2018;18(1):53. Published 2018 May 14. doi:10.1186/s12871-018-0512-x
- Jain S, Kalra S, Sharma B, Sahai C, Sood J. Evaluation of Ultrasound-Guided Transversus Abdominis Plane Block for Postoperative Analgesia in Patients Undergoing Intraperitoneal Onlay Mesh Repair. Anesth Essays Res. 2019;13(1):126-131. doi:10.4103/aer.AER_176_18
- Alsharari AF, Abuadas FH, Alnassrallah YS, Salihu D. Transversus Abdominis Plane Block as a Strategy for Effective Pain Management in Patients with Pain during Laparoscopic Cholecystectomy: A Systematic Review. J Clin Med. 2022;11(23):6896. Published 2022 Nov 22. doi:10.3390/jcm11236896
- Jin Z, Ding O, Islam A, Li R, Lin J. Comparison of Liposomal Bupivacaine and Conventional Local Anesthetic Agents in Regional Anesthesia: A Systematic Review. Anesth Analg. 2021;132(6):1626-1634. doi:10.1213/ANE.0000000000005406